Reverse Shoulder Arthroplasty · InSet® Reverse System
Reverse Shoulder Replacement in Glendale, AZ
Reverse total shoulder replacement switches the positions of the shoulder’s ball and socket so the powerful deltoid muscle, rather than the rotator cuff, lifts the arm. For patients with large rotator cuff tears, cuff tear arthropathy, complex fractures, or a failed prior surgery, it is designed to relieve pain and restore motion at the same time. Dr. James MacKenzie performs reverse shoulder replacement in Glendale, Arizona, serving Peoria, Arrowhead, Surprise, Sun City, and the Phoenix West Valley.
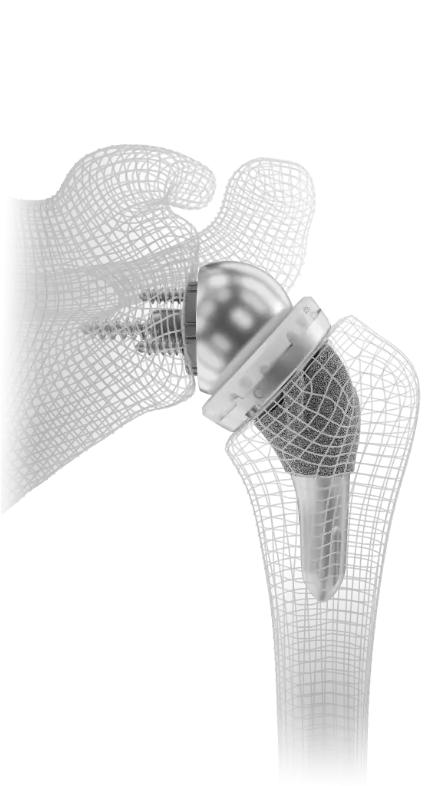
A Replacement Designed to Restore Motion, Not Just Comfort
Most joint replacements are designed to take pain away. Reverse shoulder replacement does that and something more: it is designed to give back the ability to raise the arm in shoulders that had lost it. Since its introduction in the United States in the early 2000s it has become one of the most common types of shoulder replacement in the country, and for good reason. Patients choose it to:
- Relieve the constant pain of a shoulder whose rotator cuff has failed.
- Regain the overhead reach needed to wash their hair, put dishes away, or lift a grandchild.
- Return to an active life after a shoulder problem that other operations may not be able to address.
- Address complex fractures and failed prior surgeries with a single, dependable procedure.
Understanding Your Shoulder
Your shoulder is a ball-and-socket joint formed by the humerus (upper arm bone), the scapula (shoulder blade), and the clavicle (collarbone). The humeral head is the ball; the glenoid, a shallow cup on the shoulder blade, is the socket. Smooth articular cartilage lets the two glide against each other. The rotator cuff, a group of four tendons that wrap around the ball, keeps it centered in the socket so the deltoid muscle over the top of the shoulder can raise the arm. When the cuff is healthy, this system is remarkably efficient. When the cuff is torn beyond repair, the ball rides upward, the deltoid loses its leverage, and lifting the arm becomes painful, weak, or impossible.
Conditions Reverse Shoulder Replacement Treats
A reverse replacement is generally the procedure of choice whenever the rotator cuff can no longer do its job. Dr. MacKenzie most often recommends it for:
- Cuff tear arthropathy, the combination of a massive, long-standing rotator cuff tear and the arthritis that develops as a result.
- Massive, irreparable rotator cuff tears, even without arthritis, when pain and weakness are disabling.
- Pseudoparalysis, the inability to actively raise the arm because the cuff can no longer power it.
- Complex fractures of the upper humerus, particularly in patients with thinner bone, where a reliable, predictable recovery matters most.
- Failed previous shoulder surgery, including a prior replacement or cuff repair that has not held up.
- Arthritis with a compromised cuff that could not support an anatomic implant.
How “Reverse” Works
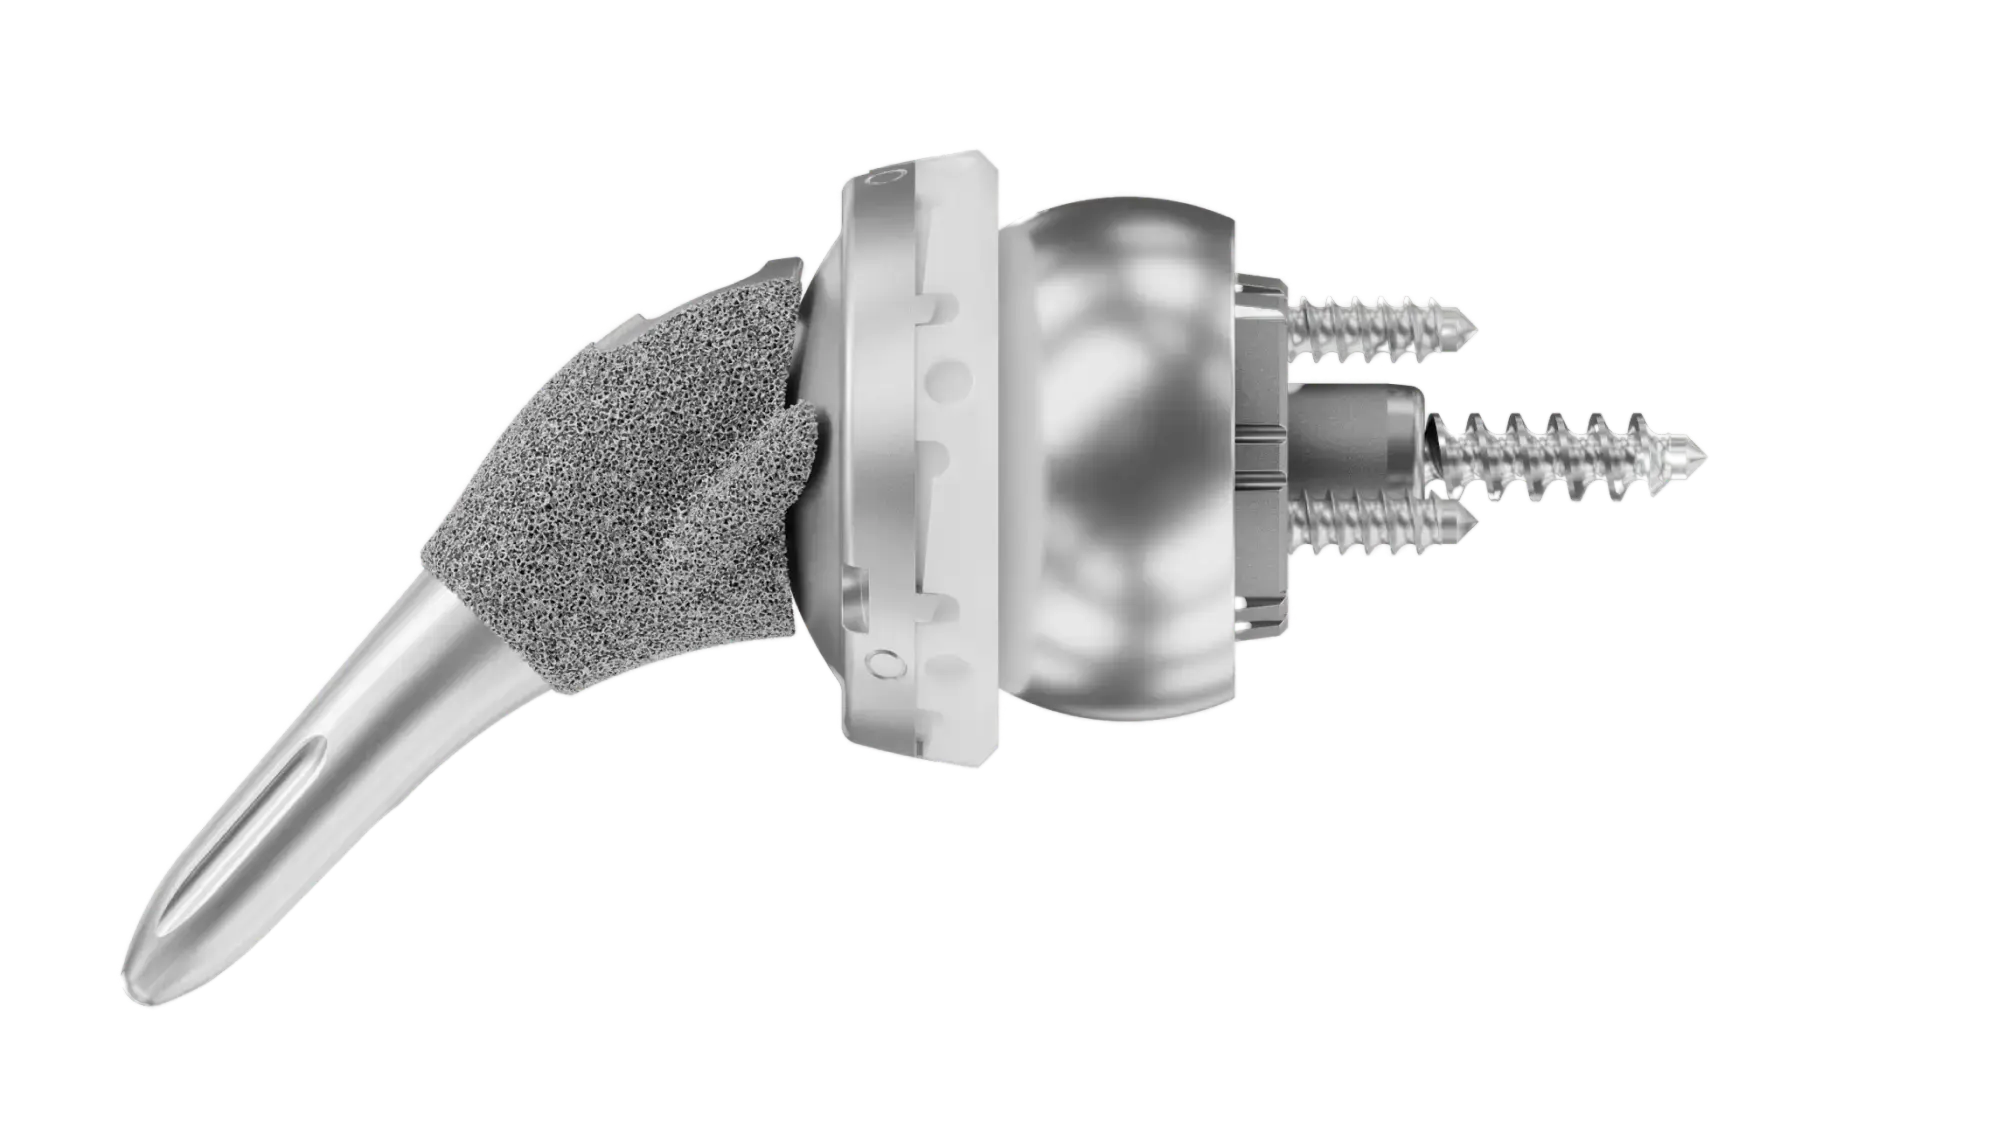
An anatomic replacement keeps the ball on the arm and the socket on the shoulder blade, and it depends on the rotator cuff to hold the ball centered. A reverse replacement changes the machine. Dr. MacKenzie places a smooth metal ball on the shoulder blade and a cupped socket on top of the arm bone. Reversing the geometry moves the center of rotation inward and downward, which gives the deltoid the leverage it needs to raise the arm on its own, without help from the rotator cuff. That is why reverse replacement may restore active motion in shoulders that other procedures cannot, and why many patients are surprised by how soon overhead reach begins to return once the deltoid takes over.
Nonsurgical Care Comes First
Before recommending surgery, Dr. MacKenzie confirms the diagnosis with X-rays and usually an MRI or CT scan, and he makes sure nonoperative options have been given a fair chance. Physical therapy to strengthen the deltoid and surrounding muscles, anti-inflammatory medication, activity modification, and corticosteroid injections all have a role. When pain and loss of function persist despite these measures, reverse replacement may offer a longer-term option for the underlying mechanical problem than conservative care can provide.
The InSet® Reverse System
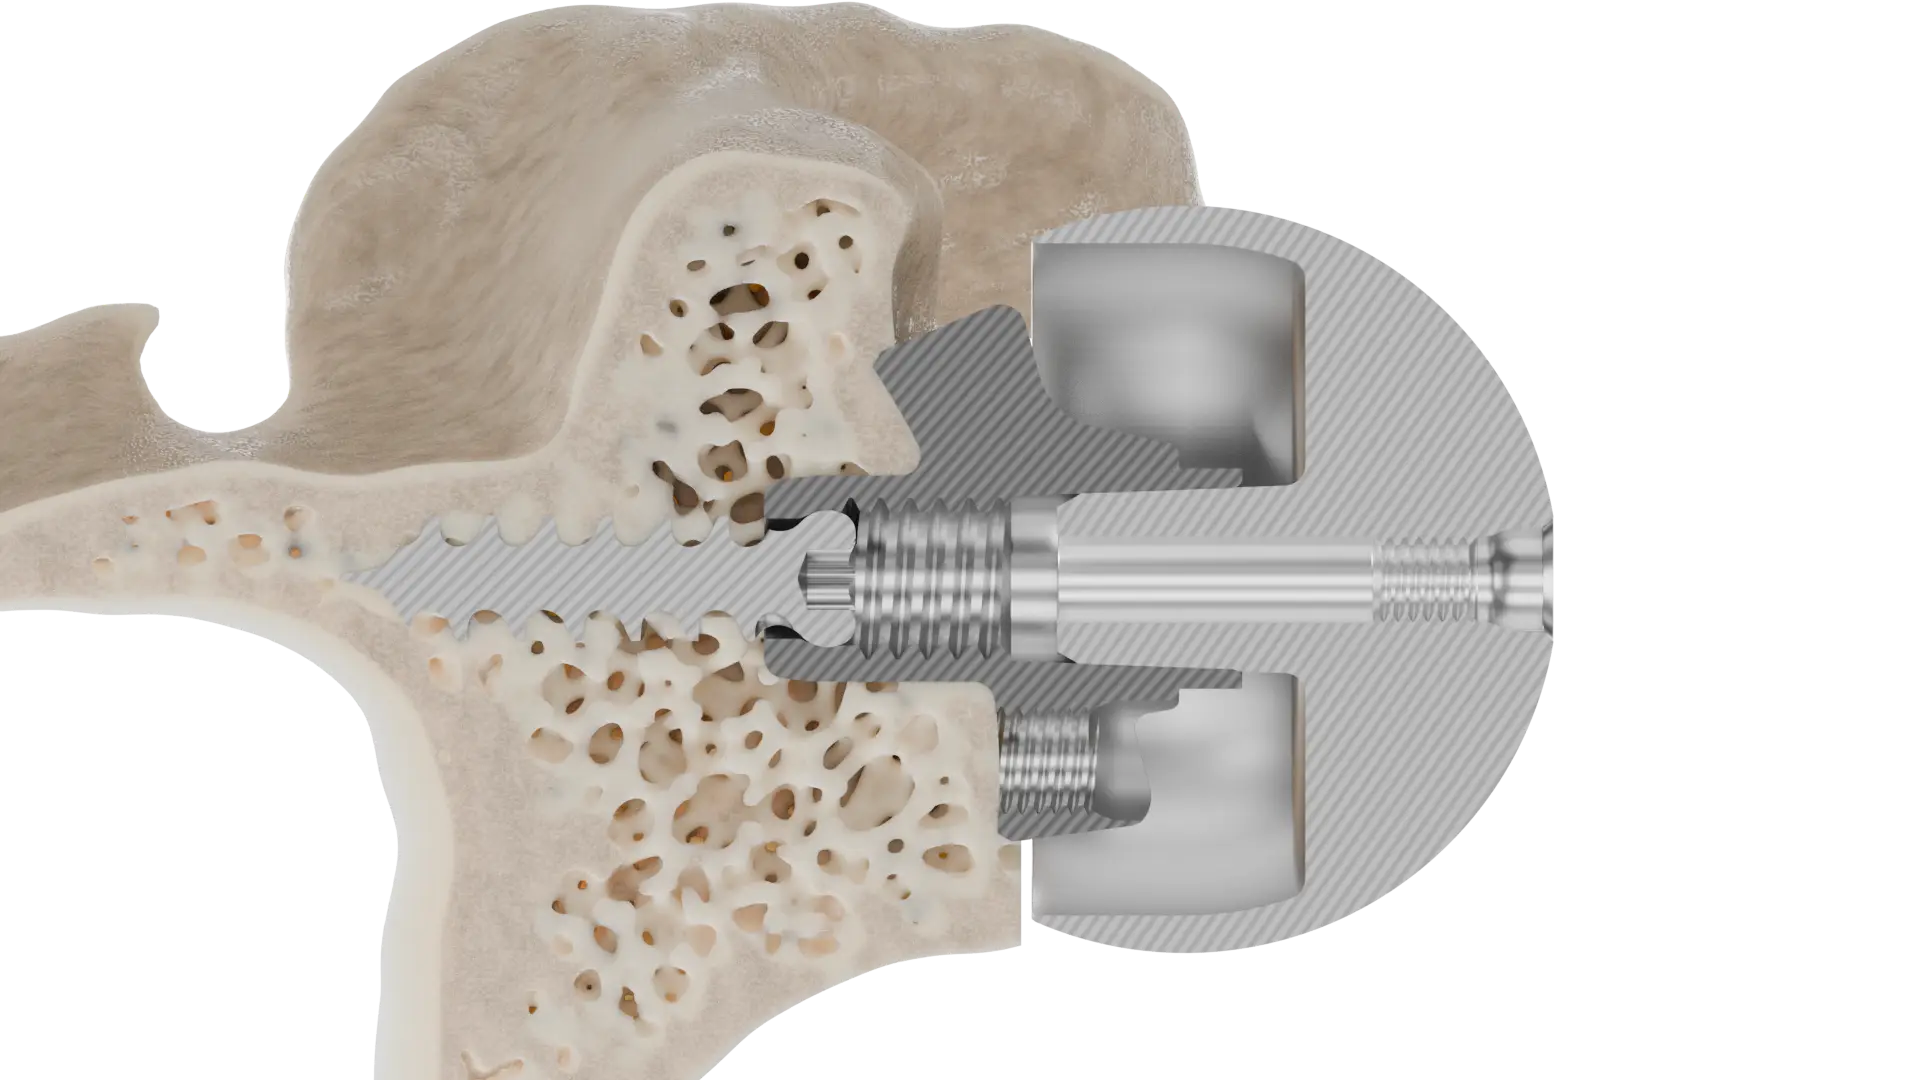
Dr. MacKenzie performs reverse replacement with the InSet® Reverse system from Shoulder Innovations, an implant system with titanium alloy components, built on the same bone-preserving philosophy as the anatomic InSet® design. Its key feature is a lateralized-lateralized design, with lateralized options on both the glenoid and humeral sides, intended to improve range of motion and post-operative function. The system offers a broad range of glenoid and humeral configurations, allowing Dr. MacKenzie to tailor the implant to your specific anatomy while removing as little of your natural bone as possible. On the humeral side, curved fins with a porous titanium coating are designed to encourage your own bone to grow into the implant and lock it in place over time. Preserving bone during the initial surgery is intended to protect your options if the shoulder ever needs further work years down the road.
Planning Your Surgery in 3D
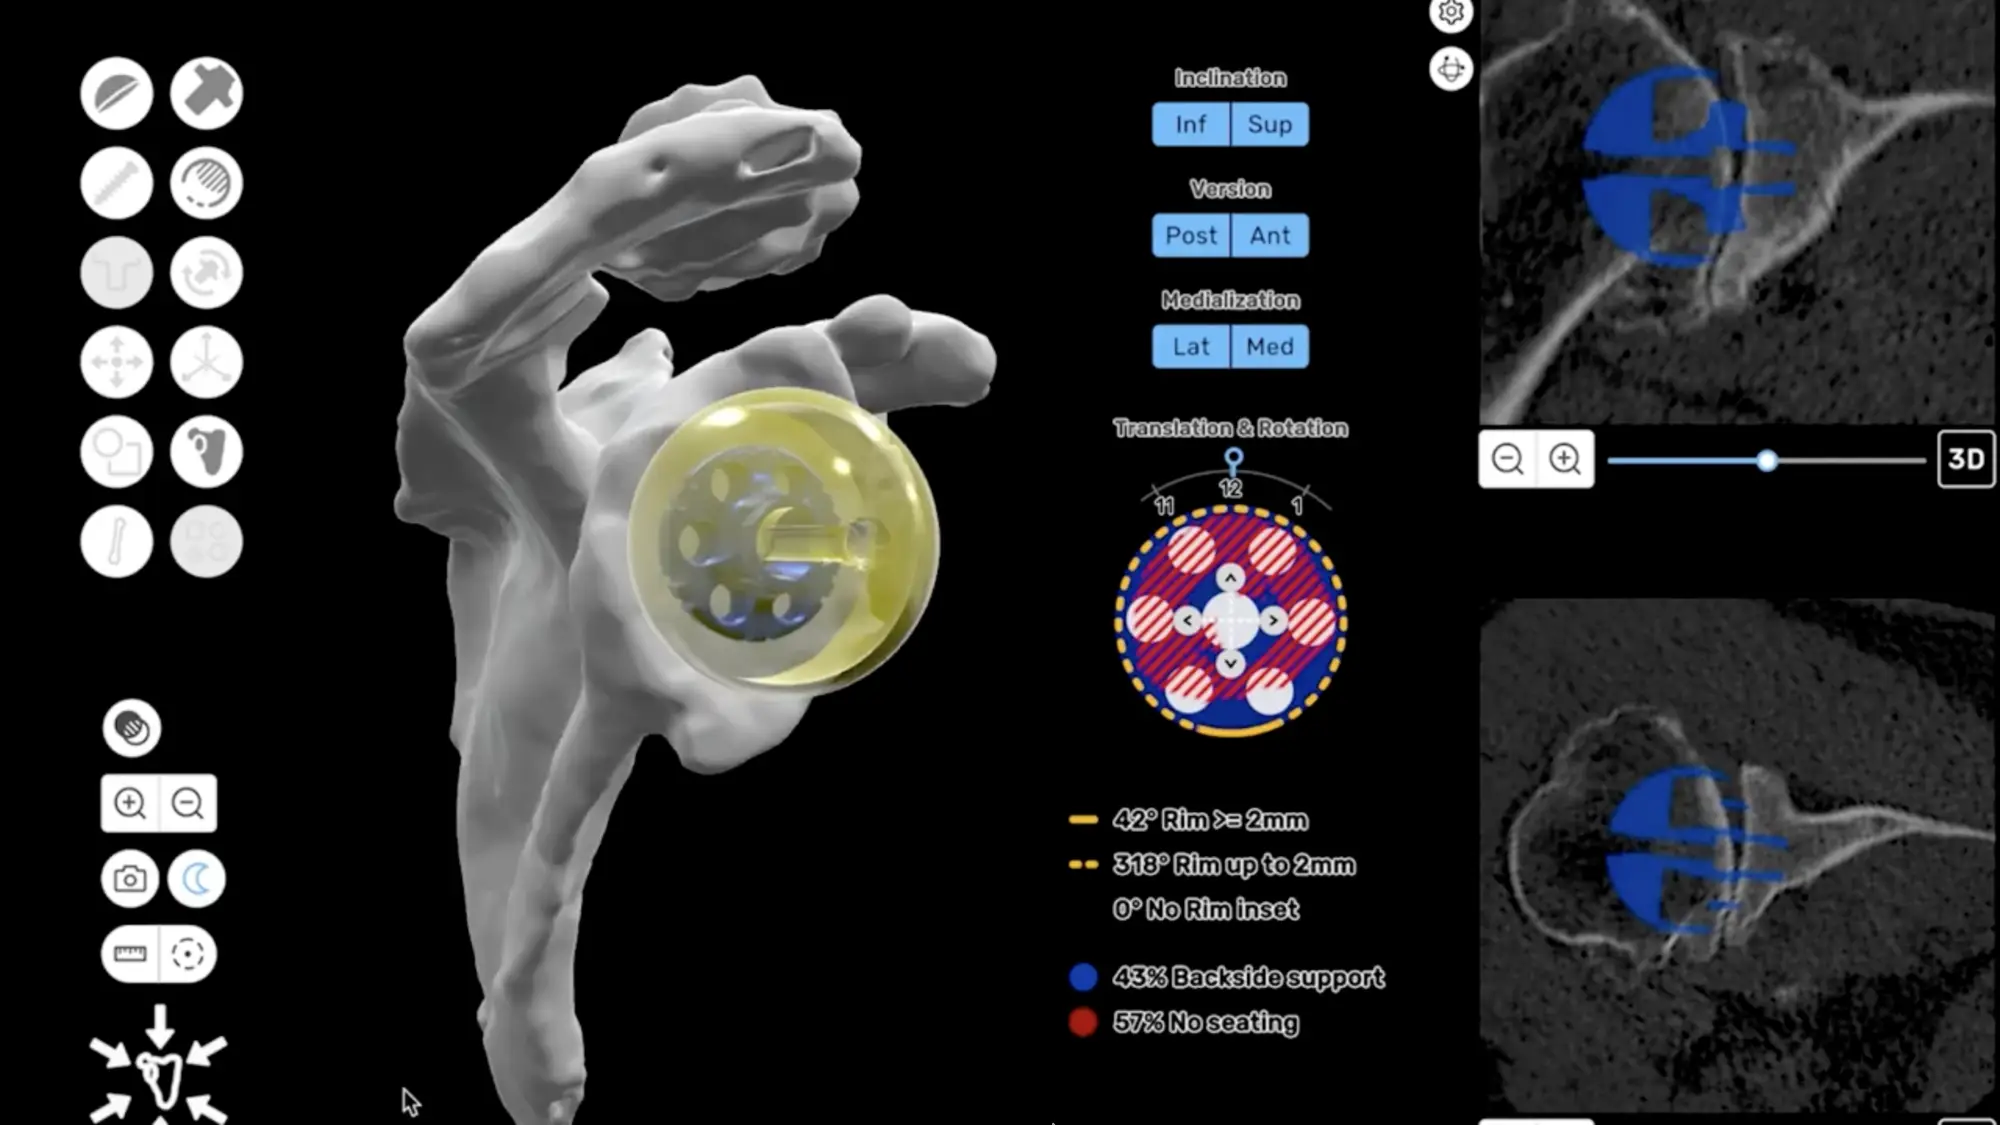
Accurate placement of the glenoid component is important to a stable, smooth-moving reverse replacement. When appropriate, Dr. MacKenzie uses CT-based three-dimensional planning software to create a computer model of your shoulder before surgery, select the component sizes, and map out their exact position and orientation in advance. Making these decisions at the planning stage is intended to support a more efficient operation and a more precisely balanced joint.
Preparing for Surgery
Once you decide to proceed, our team guides you through each step. You will complete imaging, a medical evaluation to confirm you are ready for anesthesia, and a review of your medications. You may be given exercises to keep the shoulder and deltoid as strong as possible beforehand. If you smoke, stopping before surgery may improve healing. You will receive instructions on fasting, an antiseptic wash for the shoulder, and what to bring. Arrange a ride home and someone to help with meals and dressing for the first several days. Front-opening tops and slip-on shoes make life much easier.
Surgery Day
Plan to arrive about two hours before your scheduled time. Reverse shoulder replacement is performed under general anesthesia, typically combined with a regional nerve block that keeps the shoulder comfortable well into the first day. The operation usually takes one to two hours. Dr. MacKenzie speaks with your family or friends as soon as he is finished. You wake in the recovery area with your arm in a sling, and a therapist reviews your first exercises and sling care before you go home. Many patients go home the same day; others stay one night.
Your Recovery Timeline
Recovery follows a rhythm similar to anatomic replacement, and Dr. MacKenzie’s team will personalize it to you:
Completing your physical therapy program is one of the most important things you can do to get the full benefit of your reverse replacement. Individual results vary.
- First two weeks: The sling protects the healing shoulder. Comfort is managed with the nerve block, medication, and icing, and gentle hand, wrist, and elbow exercises begin right away. Certain motions, especially reaching behind the back and pushing up from a chair, are avoided early to protect the new joint.
- Weeks two to six: Light daily activities such as eating, typing, and dressing return progressively. Therapy begins restoring motion, and many patients are already lifting the arm higher than they could before surgery.
- Weeks six to twelve: The sling comes off and deltoid strengthening begins in earnest. Driving, cooking, and most household activities resume.
- Three months to one year: Overhead function, strength, and endurance continue to build. Reaching behind the back is typically the last motion to improve, and Dr. MacKenzie will give you a clear picture of what to expect for your shoulder.
Patient Story
Hear From a Shoulder Replacement Patient
A patient shares her experience with InSet® total and reverse shoulder replacement.
Video courtesy of Shoulder Innovations. Individual results vary.
Understanding the Risks
Reverse shoulder replacement is a well-established operation, and serious complications are uncommon. General surgical risks include reactions to anesthesia, infection, bleeding, nerve or blood vessel injury, and implant wear or loosening over time. Two risks are more specific to the reverse design: dislocation, which is uncommon and can often be managed without surgery, and stress fracture of the shoulder blade near the implant. Dr. MacKenzie reviews your individual risk profile with you, and his surgical technique, implant selection, and early motion precautions are all designed to keep these risks as low as possible.
Why Patients Choose Dr. MacKenzie
Dr. MacKenzie is a board-certified, fellowship-trained orthopedic surgeon whose training spans The Johns Hopkins Hospital and a sports medicine fellowship in Miami, with experience in both manual and robotic joint replacement. His practice covers the full continuum of shoulder care, from arthroscopic rotator cuff repair through anatomic and reverse replacement. If you have been told your rotator cuff cannot be repaired, or an earlier surgery has not given you the result you hoped for, a consultation at his Glendale office can show you where you stand and what a reverse replacement could do for you. Meet Dr. MacKenzie.
Questions
Frequently Asked Questions
Don’t see your question here? Our team is happy to help.
What is reverse shoulder replacement surgery?
Reverse shoulder replacement is a joint replacement in which the ball and socket positions are switched: a metal ball is mounted on the shoulder blade and a socket on the arm bone. This lets the deltoid muscle lift the arm when the rotator cuff no longer can, which is designed to relieve pain and restore motion at the same time.
Can a torn rotator cuff be fixed with a reverse replacement?
A reverse replacement does not repair the cuff; it makes the cuff unnecessary by changing the mechanics of the joint so the deltoid powers the arm. That is exactly why it can work well for massive tears that cannot be repaired directly.
What can I expect after reverse shoulder replacement?
Many patients wear a sling for the first several weeks, begin therapy early, and regain useful overhead motion over the following months, often noticing improvement in lifting the arm surprisingly soon. Reaching behind the back is typically the last motion to return. Individual results vary.
How long does a reverse shoulder replacement last?
Reverse shoulder replacements have a strong track record, with many patients enjoying lasting pain relief and function well beyond a decade after surgery. Bone-preserving implant designs like the InSet® Reverse system are also intended to help keep future options open.
Is reverse shoulder replacement only for older patients?
Not anymore. While it was originally reserved for older patients with cuff tear arthropathy, improved implants and long-term results have made reverse replacement a dependable option for a wider range of patients, including those with complex fractures and failed prior surgeries. Dr. MacKenzie will tell you whether it is the right procedure for your shoulder.
Does insurance cover reverse shoulder replacement?
Reverse shoulder replacement for cuff tear arthropathy, irreparable cuff tears, fractures, and failed prior surgery is generally covered by insurance, including Medicare, when medically necessary. Our office verifies your benefits and answers your questions before scheduling.
Schedule a Consultation with Dr. MacKenzie
Call the office or request an appointment online and our team will help you take the next step.